Chest AI for Chest CT: Pulmonary Embolism and Aortic Dissection
Chest CT is not one exam. Suspected pulmonary embolism requires a dedicated CTPA with pulmonary timing. Incidental pulmonary embolism appears on contrast-enhanced chest, abdominal or chest-abdomen-pelvis scans with non-arterial timing, ordered for other reasons. Aortic dissection requires aortic CTA. Each situation requires a different scan and a different algorithm. Each tool was built and validated for its specific protocol.
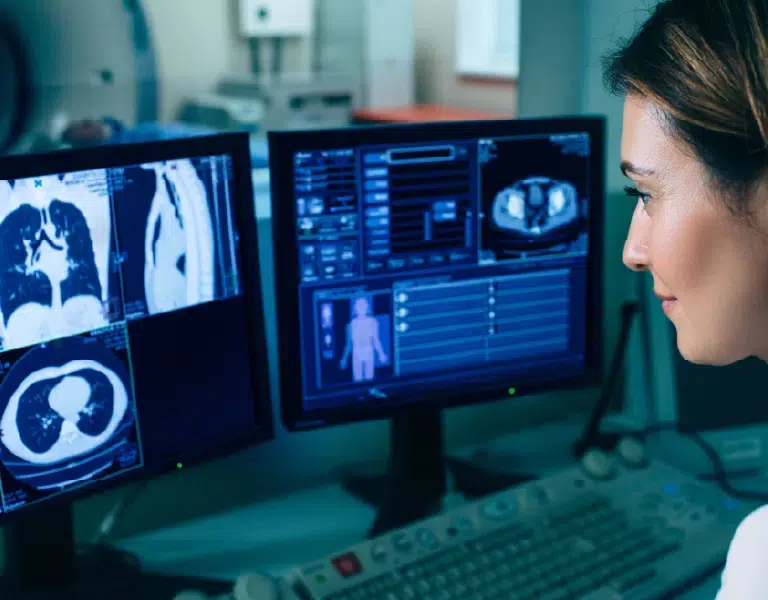
Purpose-built for their protocol.
CINA-PE
A dedicated CTPA is ordered when PE is suspected. CINA-PE flags it automatically and notifies the radiologist within a mean of one minute, before interpretation begins.
CINA-iPE
PE isn’t suspected: the scan is acquired for staging or another indication, with non-arterial timing. CINA-iPE was built for exactly this context, flagging incidental clots before discharge.
CINA-AD
Type A or Type B decides emergency surgery versus medical management. CINA-AD flags suspected dissection within seconds, and delivers the Stanford classification outside the United States.
Two tools, two points where PE can slip through.
Both detect pulmonary embolism, but for different clinical situations. Together, they cover both: the suspected PE that must be read first, and the unsuspected PE that can be overlooked.
Already on a dedicated CTPA?
That’s CINA-PE. It moves that scan to the front of the radiologist’s worklist instead of waiting behind routine studies.
View CINA-PE →Incidental findingFound on a scan ordered for something else?
That’s CINA-iPE. Built to catch the PE hiding in an oncology, trauma, or post-surgical scan that was never optimized to show it.
View CINA-iPE →Most hospitals that deploy one eventually deploy both, since running both closes both gaps.
Validated in clinical practice.
Four-hospital US health system: time-to-consult and in-hospital mortality measured before and after CINA-PE.
At Gustave Roussy, 3,047 oncology surveillance scans: how often incidental PE was overlooked without AI, and what changed with CINA-iPE.
Multi-reader, multi-case study: effect of AI-assisted notification on the time from scan acquisition to a completed clinical assessment.
A Customer’s Perspective
“In addition of being a high-performance software, Avicenna.AI gives access to patient results usually within 2 to 5 minutes, thus allowing radiologists to accelerate time of interpretation, providing a better service for our hospitals and better patient outcomes.”

Your questions, answered
Do I need to deploy all three tools together?
No, each deploys independently. Running all three covers chest emergencies end to end on the protocols your department already acquires.
Does this integrate with our existing PACS?
Yes. All three tools integrate via standard DICOM and run automatically on qualifying scans, with no manual trigger and no change to your existing workflow.
Who makes the final call?
The radiologist, always. CINA flags and prioritizes suspected cases so they reach the right reader faster. Every case is still reviewed, interpreted and confirmed by a radiologist.
Explore the other AI suites.
Stroke, PE, aortic dissection, cervical fracture

Stroke and head CT
Cervical and vertebral fractures

Head and cervical spine in trauma
Findings on scans ordered for something else